Quick answer: NPH vs dementia comes down mainly to the order and type of symptoms doctors see. In NPH, walking difficulty comes first and thinking is slowed rather than densely forgetful. In Alzheimer’s, memory fails well before gait changes. Brain imaging showing enlarged ventricles without matching brain shrinkage supports NPH.
Key Takeaways
- Symptom order is the single most useful clue: gait first suggests NPH.
- NPH causes slowed processing; Alzheimer’s causes dense recent-memory loss.
- Imaging in NPH shows enlarged ventricles out of proportion to brain atrophy.
- A CSF tap test can support the diagnosis and predict shunt response.
- NPH and dementia can coexist, which complicates the picture.
A man I corresponded with online spent the better part of a year convinced his mother had Alzheimer’s, because that was the diagnosis her GP gave first. It made sense on paper. She was seventy-nine. She had started forgetting appointments and repeating questions.
What did not make sense, to him, was the order things had happened in. Her walking had changed months before the memory trouble started — short, shuffling steps, a wider stance, as though the floor might tilt. He mentioned this to two different doctors before a third one finally asked the question that changed everything: which came first, the walking or the memory?
That single question turned out to be most of what separates normal pressure hydrocephalus from Alzheimer’s disease, and it is worth understanding exactly why.
NPH vs Dementia: Why the Two Are Confused So Often
It is easy to see why his mother’s doctor reached for Alzheimer’s first.
Both conditions affect older adults. Both cause memory complaints, apathy and slowing. Both progress over months to years. Consequently, the initial impression frequently lands on dementia.
The Alzheimer’s Association notes explicitly that because NPH symptoms resemble Alzheimer’s, Parkinson’s and Creutzfeldt-Jakob disease, NPH is often overlooked or misdiagnosed. This is not a rare oversight — it is the norm.
The Order of Symptoms Is the Biggest Clue
In NPH, the classic sequence is walking, then thinking, then bladder. Families often describe a relative who became unsteady months before anyone worried about memory.
In Alzheimer’s disease, that order is reversed. Memory and word-finding decline first, and walking usually stays normal until much later in the illness.
Therefore, when a family says “the walking went first”, that history deserves specific attention rather than being folded into a general picture of decline.
This was exactly the history he gave, almost word for word, once someone finally asked for it in order rather than as a general list of worries.
How the Walking Itself Differs
The NPH gait has a recognisable character. Steps are short and shuffling, the feet stay close to the ground as if magnetised, and the stance is wide. Turning is particularly revealing — it takes multiple small steps rather than one smooth pivot.
Parkinson’s disease also causes shuffling, but usually with a stooped posture, reduced arm swing on one side, and a resting tremor. Additionally, Parkinson’s gait tends to be narrow-based, whereas NPH is wide-based.


What Brain Imaging Shows
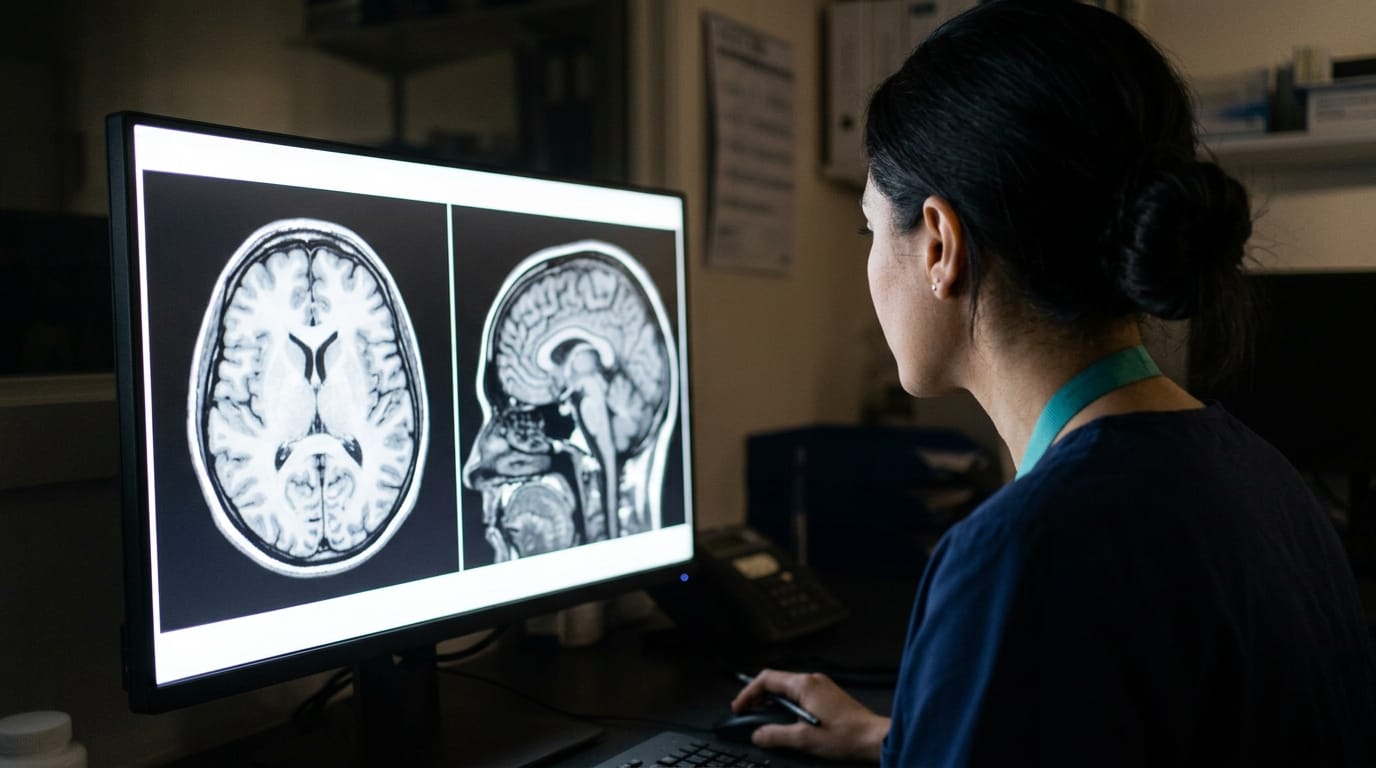
On CT or MRI, NPH shows enlarged ventricles that are out of proportion to any shrinkage of brain tissue. In dementia caused by atrophy, ventricles enlarge because the brain around them is shrinking — a different pattern radiologists can usually distinguish.
Radiologists may also measure the Evans index, comparing ventricle width to skull width, and look for tight sulci at the top of the brain. No single measurement is definitive, so imaging is interpreted alongside the clinical history.
The Tap Test and What It Can and Cannot Tell You
A lumbar puncture removes a modest volume of cerebrospinal fluid, and walking is measured before and afterwards. Clear temporary improvement suggests a shunt is likely to help.
However, research using wearable motion sensors has noted that the predictive capacity of the tap test remains debated. A negative result does not reliably exclude benefit, and some centres proceed to extended lumbar drainage over several days when suspicion remains high.
This is worth knowing, because families are sometimes told a single negative tap test closes the question. It does not always.

When Both Conditions Are Present
The NPH vs dementia distinction can blur, since NPH and Alzheimer’s can coexist, particularly in the over-75s. In that situation a shunt may improve walking and continence while having little effect on memory.
That is still a meaningful gain. Restored mobility reduces falls and often allows someone to stay at home longer, even if cognition does not change.
Frequently Asked Questions
How do doctors tell NPH from Alzheimer’s?
Doctors look at the order of symptoms, the walking pattern, and brain imaging. NPH typically starts with gait difficulty and causes slowed thinking, while Alzheimer’s starts with memory loss. Imaging in NPH shows enlarged ventricles out of proportion to brain shrinkage.
Can NPH be mistaken for Parkinson’s disease?
Yes, frequently. Both cause shuffling and difficulty starting movement. Parkinson’s usually adds a resting tremor, stooped posture and reduced arm swing, and the gait is narrow-based. NPH gait is wide-based and improves little with Parkinson’s medication.
Does NPH show up on a CT scan?
Yes. A CT scan shows enlarged ventricles, which is the main structural finding in NPH. However, enlarged ventricles alone do not confirm the diagnosis, because they also occur with normal ageing and brain atrophy. Imaging must be read alongside symptoms.
Can you have both NPH and dementia?
Yes. The two can coexist, especially in older patients. In that case, shunt surgery may improve walking and bladder control while memory remains unchanged. Improved mobility is still a worthwhile outcome for many families.
Is NPH reversible?
Symptoms can improve substantially after shunt surgery, particularly walking. Complete reversal is less common, and results are usually better when treatment happens early rather than after years of symptoms.
His mother had her shunt fitted four months after that third doctor’s question. Her walking improved within weeks; her memory took longer, and never fully returned to where it had been before the delay. He does not blame the first two doctors exactly, but he still brings up, whenever he can, how much of that year might have been recovered by one question asked earlier.
If someone in your family was told “probably dementia” without much explanation, it is fair to ask what order the symptoms came in — and worth writing the answer down before the appointment, not during it.
Related Reading
- Normal Pressure Hydrocephalus: 7 Signs Families Miss
- Hydrocephalus in Adults: Symptoms and Treatment
- Hydrocephalus CT Scan and MRI: What the Images Show
Bibliography
- Alzheimer’s Association. Normal Pressure Hydrocephalus (NPH). Available at: alz.org
- Gait apraxia evaluation in normal pressure hydrocephalus using inertial sensors. Fluids and Barriers of the CNS. 2022. Available at: PMC9219204
- Cerebrospinal fluid tap test in normal pressure hydrocephalus. Available at: PubMed 42285766
- Hydrocephalus Association. What is Normal Pressure Hydrocephalus? Available at: hydroassoc.org