
Quick answer: ETV (endoscopic third ventriculostomy) creates a new drainage pathway inside the brain without implanted hardware, while a VP shunt drains fluid through a permanent tube to the abdomen. Neither is universally “better” — ETV suits specific anatomy, mainly obstructive hydrocephalus in older infants and children, while VP shunts remain standard for most other cases. Recent meta-analyses show comparable survival and pressure control, with ETV showing lower infection rates.
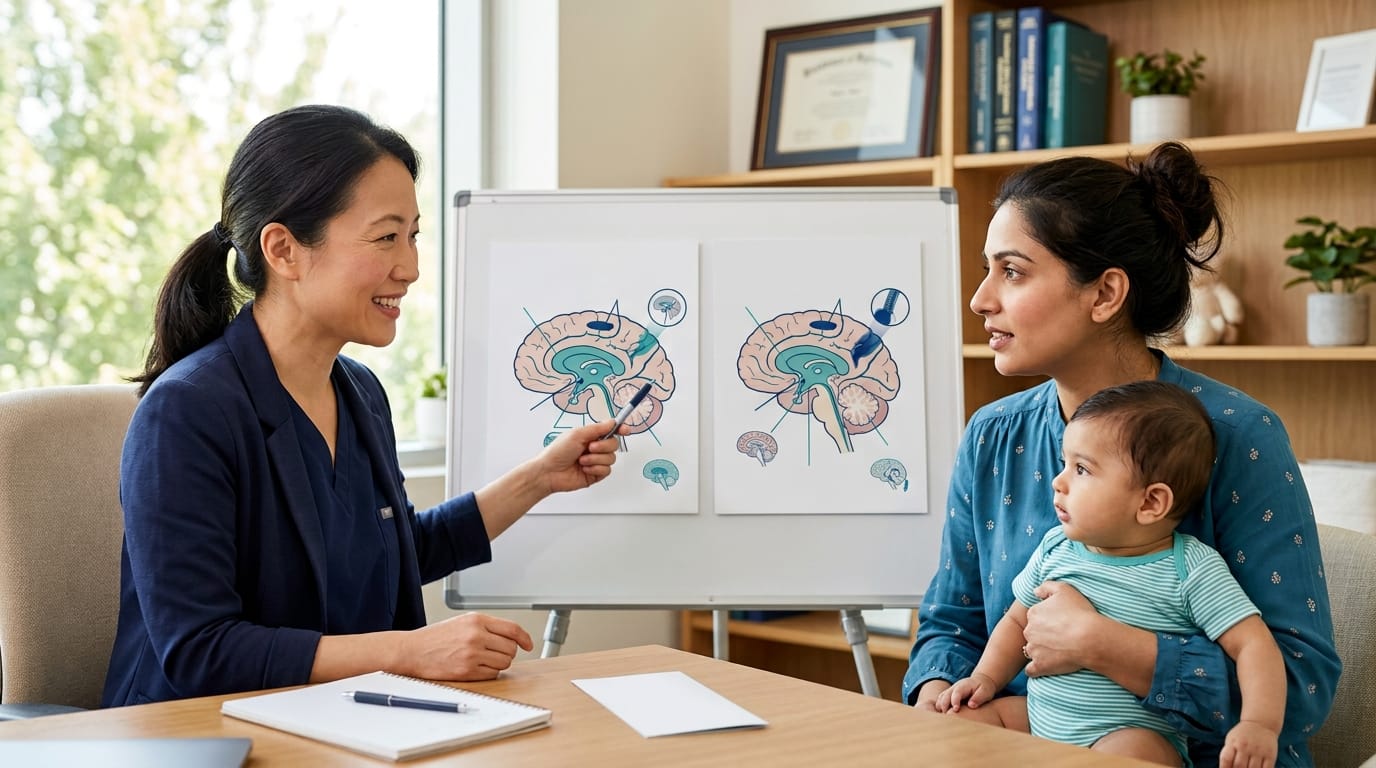
Our neurosurgeon drew two diagrams on the back of a consent form, one for each option, and I remember being grateful for the drawing and frustrated by the decision at the same time. There is no universally right answer here. There is a right answer for your child’s specific anatomy, age, and cause of hydrocephalus, and that is a genuinely different question for every family that hears it.
What Each Procedure Actually Does
A ventriculoperitoneal (VP) shunt is a system of tubing that drains excess cerebrospinal fluid (CSF) from the brain’s ventricles to the abdominal cavity, where the body reabsorbs it. It includes a valve that regulates flow and stays in place, typically for life, sometimes with revisions. Endoscopic third ventriculostomy (ETV), in contrast, uses a small camera to create a new opening in the floor of the third ventricle, allowing CSF to bypass a blockage and flow along a more natural pathway. There is no implanted hardware left behind with a successful ETV — which is exactly why it appeals to so many families once they understand it.
Who Is Actually a Candidate for ETV?
ETV works only when there is an obstruction the new pathway can bypass — most commonly aqueductal stenosis or hydrocephalus caused by a posterior fossa tumor. It is generally more successful in children over six months of age; younger infants have historically had higher ETV failure rates, partly due to less mature CSF absorption pathways. It is not typically an option for communicating hydrocephalus, where the problem is fluid reabsorption rather than a blockage a new channel could bypass.

What the Research Actually Shows
According to PubMed, a 2026 updated meta-analysis pooling 12 studies and 917 pediatric patients with hydrocephalus from posterior fossa tumors found no statistically significant difference between ETV and VP shunt in mortality, control of intracranial pressure, or need for reoperation. However, ETV was associated with a significantly lower infection rate (OR 0.15) and lower incidence of bleeding complications (OR 0.40) (Lino-Filho et al., Child’s Nervous System, 2026; DOI). A separate 2025 analysis of the U.S. National Inpatient Sample, covering 5,305 pediatric patients, found ETV patients had lower odds of a prolonged hospital stay, lower total hospital charges, and a higher likelihood of routine discharge home compared with VP shunt patients, with no significant difference in mortality (Salik et al., Child’s Nervous System, 2025; DOI). Neither study found ETV was simply “better” across the board — the advantages were specifically around infection and resource use, not survival.
The Trade-Off Nobody Puts on the Consent Form Clearly Enough
A VP shunt, once placed, carries an ongoing lifelong risk of mechanical failure or infection, requiring revision surgery — sometimes more than once over a child’s lifetime. ETV avoids that specific long-term hardware risk entirely, but it carries its own risk: the new opening can, less commonly, narrow or close over months or years, requiring either a repeat ETV or a shunt after all. In other words, ETV is not “shunt-free forever” for every child who initially succeeds with it — it is a genuine alternative with its own separate long-term monitoring needs, which is a nuance that gets lost in hallway conversations far too often.

What This Means for Your Family
If your neurosurgeon is offering ETV as an option, it usually means your child’s imaging shows a blockage in a location ETV can actually reach and bypass — which is itself informative about your child’s specific type of hydrocephalus. If ETV is not being offered, it is worth asking directly why, since the answer (communicating hydrocephalus, age under six months, or anatomy that makes the procedure unsafe) tells you something important about what is actually happening inside your child’s brain.
Questions to Ask Your Doctor
- Is my child’s hydrocephalus obstructive or communicating, and does that change which option is available?
- What is the specific success rate for ETV in a child of my child’s age and diagnosis?
- If ETV fails, is a shunt still fully available as a backup, and would that delay treatment?
- What does follow-up monitoring look like differently for ETV versus a shunt?
- Has this surgical team performed enough ETVs to have meaningful outcome data for children like mine?

Frequently Asked Questions About ETV vs VP Shunt
Is ETV less invasive than a VP shunt?
In the sense that it leaves no permanent implanted hardware, yes. Both are still real neurosurgical procedures with real risks, and neither should be thought of as minor.
Can a failed ETV be converted to a shunt later?
Yes. If an ETV narrows or fails to adequately control CSF pressure, a VP shunt remains available as a backup option, typically without added risk from the prior ETV procedure.
Does ETV work for babies under six months old?
It can, but historical success rates are lower in very young infants, partly due to less mature CSF pathways. Many surgeons weigh this age factor carefully before recommending ETV in this age group.
Which option has a lower infection risk?
Meta-analysis data shows ETV is associated with a significantly lower infection rate than VP shunt placement, likely because there is no permanent foreign material left in place.
The two diagrams on that consent form are still, somewhere, in a folder in our house. I look at them sometimes and think about how much clearer the decision felt once someone explained why the option even existed for our son’s specific anatomy — not just that it existed. If you are facing this choice, ask for that same specificity.
This article is written for informational purposes only and does not constitute medical advice. Always consult your neurologist, paediatrician, or qualified healthcare provider for diagnosis and treatment decisions specific to your child’s situation. Read our full medical disclaimer at braincarepath.com/disclaimer/
Bibliography
- Lino-Filho AM, da Silva Andrade WM, de Morais WJ, et al. Endoscopic third ventriculostomy versus ventriculoperitoneal shunt in the treatment of hydrocephalus due to posterior fossa tumors in children: an updated meta-analysis. Child’s Nervous System. 2026;42(1):9. Available at: https://doi.org/10.1007/s00381-025-07113-8
- Salik I, Larin B, Choe I, et al. An analysis of short-term outcomes and healthcare resource utilization for ventriculoperitoneal shunt versus endoscopic third ventriculostomy in pediatric patients with hydrocephalus following posterior fossa brain tumor resection. Child’s Nervous System. 2025;41(1):343. Available at: https://doi.org/10.1007/s00381-025-07015-9
- Hydrocephalus Association. Treatment Options for Hydrocephalus. Available at: https://www.hydroassoc.org/