

Quick answer: Premature babies, especially those born before 32 weeks, are at higher risk of a specific type of hydrocephalus caused by bleeding into the brain’s ventricles — intraventricular hemorrhage (IVH). Not every bleed leads to hydrocephalus, and severity varies widely; routine cranial ultrasounds in the NICU are how it is typically caught early.
The NICU has its own vocabulary, delivered fast, often at 3am, by whoever is on call. “Grade” and “IVH” were two of the first words we learned there, weeks before “hydrocephalus” entered the conversation at all. If your child is in the NICU right now and someone has just mentioned a bleed, this is the explanation I wish had come with it.
Why Prematurity and Hydrocephalus Are Connected
The connection runs through a fragile structure called the germinal matrix, a network of tiny, poorly supported blood vessels present in the developing brain that is most vulnerable between roughly 24 and 32 weeks’ gestation. In a preterm infant, these vessels can rupture — an intraventricular hemorrhage — often in the first days of life, triggered by the general instability of very early birth: blood pressure swings, breathing difficulties, or simple handling stress. When enough blood enters the ventricles, it can disrupt normal CSF flow and reabsorption, leading to what is specifically called post-hemorrhagic hydrocephalus.
Understanding the Grading System
IVH is graded I through IV by cranial ultrasound, with grade I representing a small, localized bleed and grade IV representing bleeding that extends into the surrounding brain tissue itself. Grades I and II frequently resolve without hydrocephalus developing at all. Grades III and IV carry meaningfully higher risk of post-hemorrhagic hydrocephalus, though even within these more severe grades, outcomes vary considerably from child to child — the grade alone does not determine your child’s individual trajectory.
How Common Is This, Actually?
Rates vary by gestational age and birth weight, with the highest risk concentrated in the most extremely premature infants. According to PubMed, a 2026 retrospective cohort study at a Middle Eastern Level III NICU examined infants born at or before 30 weeks’ gestation, or under 1500 grams, and found that implementing a structured ten-component neuroprotective “Brain Care Bundle” — covering measures like delayed cord clamping, midline head positioning, minimal handling, and permissive hypercapnia — reduced severe IVH incidence from 15% to 5% (Almazrooei et al., Pediatric Neurology, 2026). That is a striking reduction, and it reflects a broader shift in NICU care: a real, growing portion of severe IVH may be preventable through structured, consistent bedside practices rather than being purely a matter of chance tied to gestational age.

How Post-Hemorrhagic Hydrocephalus Is Monitored and Treated
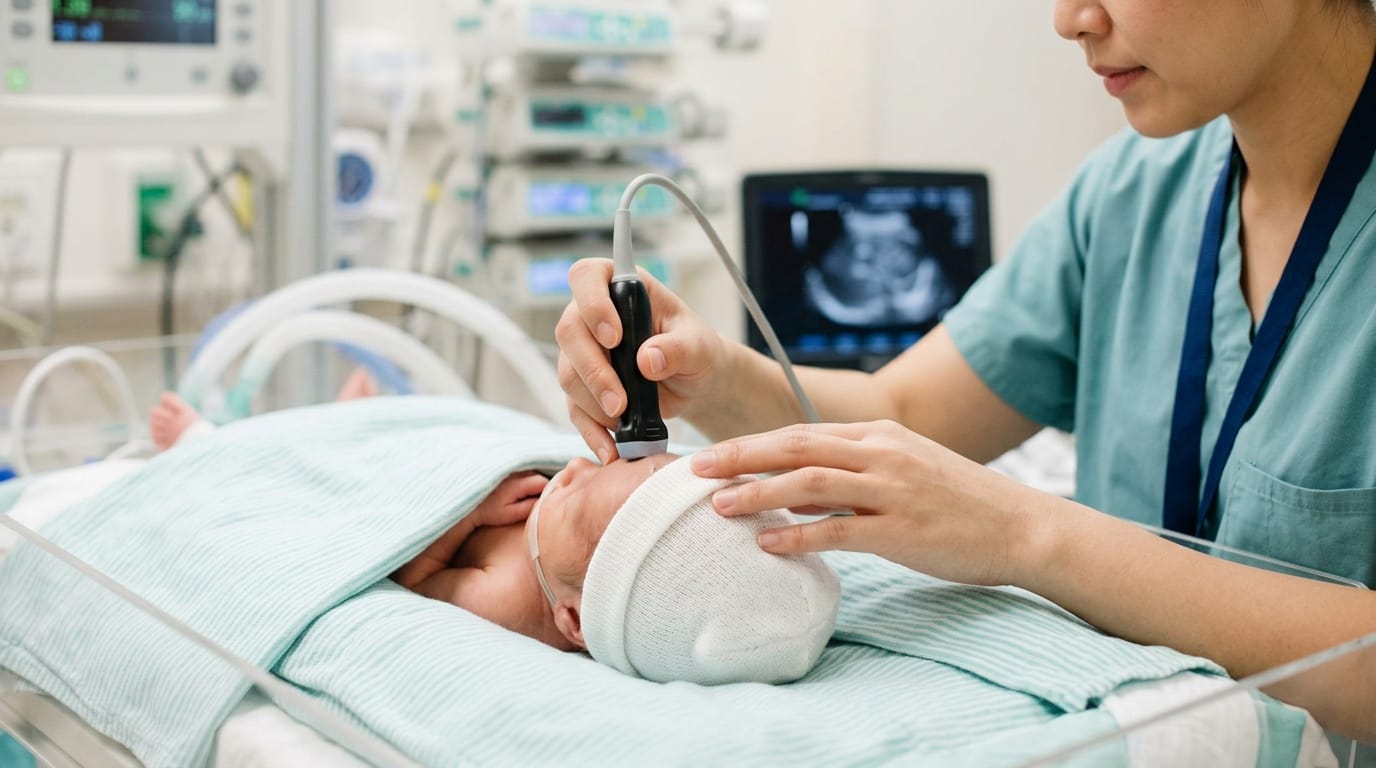
Infants with IVH undergo serial cranial ultrasounds, often weekly or more frequently, to track ventricle size over time. If hydrocephalus progresses, treatment approaches range from temporary measures — such as a ventricular reservoir or repeated lumbar punctures to remove excess fluid while the infant grows large enough for more definitive surgery — to eventual permanent shunt placement once the baby is medically stable enough for the procedure, often after reaching a certain weight threshold.
What This Means for Your Family
If your baby has an IVH diagnosis without hydrocephalus yet, ongoing ultrasound monitoring does not mean hydrocephalus is inevitable — many grade I and II bleeds resolve on their own. If hydrocephalus has developed, the NICU team’s approach of temporizing measures before permanent shunt placement reflects a genuine effort to wait until surgery carries the lowest possible risk for your baby, not a delay in addressing the problem. Either way, ask the NICU team directly what grade of bleed your baby has and what specific findings they are watching for on each ultrasound — the vocabulary becomes less frightening once it is attached to a concrete picture of your own child’s situation.

Questions to Ask the NICU Team
- What grade of IVH does my baby have, and on which side or sides of the brain?
- What ventricle size or growth rate would prompt intervention?
- If hydrocephalus develops, what temporizing options are being considered before a permanent shunt?
- What neuroprotective measures is this NICU using, and how does that affect our baby’s risk?
- What does long-term neurodevelopmental follow-up look like for a baby with this grade of IVH?

Frequently Asked Questions About Hydrocephalus in Premature Babies
Does every premature baby with a brain bleed develop hydrocephalus?
No. Many bleeds, especially lower-grade ones, resolve without ever causing hydrocephalus. Only a portion of infants with IVH go on to develop post-hemorrhagic hydrocephalus.
How is IVH found in a premature baby?
Through routine cranial ultrasounds performed at the bedside in the NICU, typically starting in the first week of life and repeated on a regular schedule for at-risk infants.
Can post-hemorrhagic hydrocephalus be prevented?
Not entirely, but structured neuroprotective care practices in the NICU have been shown to meaningfully reduce the rate of severe IVH, which is the primary risk factor for this specific type of hydrocephalus.
Will my premature baby need a shunt immediately if hydrocephalus develops?
Not necessarily. Many NICUs use temporary measures, such as a ventricular reservoir, to manage fluid buildup until the baby is large and stable enough for permanent shunt surgery.
Those early NICU weeks compress an enormous amount of new vocabulary into an already exhausting time. If “IVH” is a word you have just learned, you are not behind — you are exactly where every parent in that unit starts.
This article is written for informational purposes only and does not constitute medical advice. Always consult your neurologist, paediatrician, or qualified healthcare provider for diagnosis and treatment decisions specific to your child’s situation. Read our full medical disclaimer at braincarepath.com/disclaimer/
Bibliography
- Almazrooei A, Balubaid Y, Alkafi N, Abu Zaid M, Aljeaid R, Abuaouf M. Impact of a Structured Brain Care Bundle on Severe Germinal Matrix Hemorrhage-Intraventricular Hemorrhage in Very Preterm Neonates: A Retrospective Cohort Study. Pediatric Neurology. 2026;178:164-169. Available at: https://doi.org/10.1016/j.pediatrneurol.2026.02.011
- De Rose DU, Martini L, Ronchetti MP, et al. Case Report: Congenital neurosyphilis presenting as post-hemorrhagic hydrocephalus in a preterm infant and a review of literature. Frontiers in Pediatrics. 2025;13:1675980. Available at: https://doi.org/10.3389/fped.2025.1675980
- Hydrocephalus Association. Post-Hemorrhagic Hydrocephalus in Premature Infants. Available at: https://www.hydroassoc.org/