
Quick answer: Aqueductal stenosis is a narrowing of the thin channel connecting the brain’s third and fourth ventricles, blocking cerebrospinal fluid flow and causing hydrocephalus. Dandy-Walker malformation is a different congenital condition involving underdevelopment of the cerebellum and an enlarged fourth ventricle, which can also cause hydrocephalus. Both are among the most common causes of congenital hydrocephalus diagnosed prenatally or at birth.
The ultrasound technician went quiet in a specific way that every parent who has been through a prenatal scan learns to recognize immediately, long before any doctor says a word. For families later told it is aqueductal stenosis or Dandy-Walker malformation, that quiet moment is often the first sign, weeks or months before anyone explains what either term actually means.
What Aqueductal Stenosis Actually Is
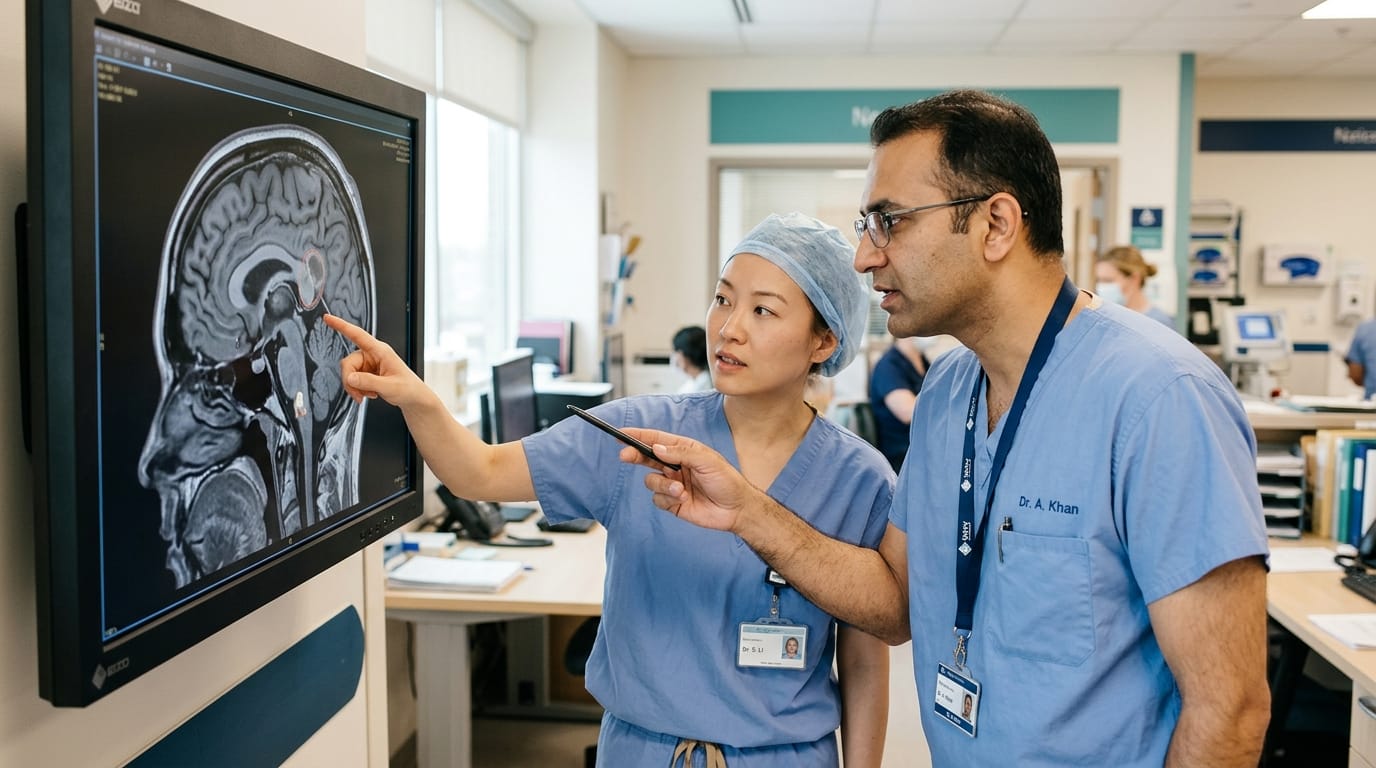
The cerebral aqueduct is a narrow channel, only a few millimeters wide even in a typically developing brain, that connects the third ventricle to the fourth ventricle, allowing cerebrospinal fluid to flow through on its normal path. Aqueductal stenosis is a narrowing or blockage of this specific channel — sometimes from a congenital malformation, sometimes from scarring after infection or bleeding, and in a smaller subset of cases, from an inherited X-linked genetic condition that primarily affects boys. Whatever the specific cause, the result is the same: fluid backs up behind the blockage, the ventricles enlarge, and hydrocephalus develops.
What Dandy-Walker Malformation Actually Is
Dandy-Walker malformation is a distinct congenital condition involving three features together: underdevelopment (or complete absence) of the cerebellar vermis, the structure connecting the two halves of the cerebellum; an enlarged fourth ventricle; and an enlarged space at the back of the skull, sometimes visible on imaging as a posterior fossa cyst. Hydrocephalus develops in a majority of Dandy-Walker cases, though not universally, because the same structural changes that define the malformation can also disrupt normal CSF flow and reabsorption.

How These Are Actually Diagnosed
Both conditions are frequently detected on routine prenatal ultrasound, often as early as the second trimester, and are typically confirmed with fetal MRI, which offers considerably more detail about the specific structures involved. For families receiving one of these diagnoses prenatally, a fetal MRI referral to a center with pediatric neurosurgery and maternal-fetal medicine expertise is a reasonable and common next step, allowing more informed conversations about what to expect after birth.

What the Severity Range Actually Looks Like
This is the part that gets flattened in a quick hallway conversation and deserves more room: both aqueductal stenosis and Dandy-Walker malformation exist on a real spectrum. Some children with aqueductal stenosis have mild, slowly progressive hydrocephalus managed with a single shunt placement and go on to have typical development. Others have more severe presentations requiring more intensive early intervention. Dandy-Walker malformation shows similarly wide variation — some children have normal or near-normal cognitive development, while others, particularly those with more extensive cerebellar involvement or additional brain anomalies, face more significant developmental challenges. A prenatal diagnosis alone does not reliably predict which end of that range a specific child will fall on.
What This Means for Your Family
If you have just received either diagnosis, it is reasonable to feel like you are being asked to make major decisions from a position of real uncertainty — because you are. Ask specifically what other structures on the imaging look typical or atypical, since isolated aqueductal stenosis or Dandy-Walker malformation, without other brain anomalies present, generally carries a different outlook than the same finding alongside additional structural differences. That distinction is one of the most useful questions a family can ask a maternal-fetal medicine specialist or pediatric neurosurgeon at this stage.

Questions to Ask Your Doctor
- Is this an isolated finding, or are there other structural differences visible on the imaging?
- For aqueductal stenosis specifically, is genetic testing for X-linked hydrocephalus being recommended, and why?
- What does the range of outcomes actually look like for a case with these specific imaging findings?
- Will treatment be needed immediately after birth, or will we monitor first?
- Which specialists should be involved in delivery planning given this diagnosis?
Frequently Asked Questions About Aqueductal Stenosis and Dandy-Walker
Is aqueductal stenosis always genetic?
No. It can result from a genetic cause, particularly a rarer X-linked form affecting mostly boys, but it can also result from scarring after infection, bleeding, or tumors, or occur without any identifiable cause at all.
Does Dandy-Walker malformation always cause hydrocephalus?
No, though hydrocephalus develops in a majority of cases. Some children with Dandy-Walker malformation never develop hydrocephalus and require no CSF diversion procedure.
Can these conditions be detected before birth?
Yes, both are frequently identified on routine prenatal ultrasound and typically confirmed with a more detailed fetal MRI.
Does a prenatal diagnosis predict how a child will develop?
Not reliably on its own. Outcomes vary considerably, and whether other brain structures are affected alongside the primary finding matters more than the diagnosis label alone.
That quiet moment during our own ultrasound, years ago now, turned out to be about something else entirely for our family. But I remember exactly how it felt to sit in it without an explanation, and if you are in that moment right now with one of these two diagnoses, I hope this filled in some of what a rushed appointment could not.
This article is written for informational purposes only and does not constitute medical advice. Always consult your neurologist, paediatrician, or qualified healthcare provider for diagnosis and treatment decisions specific to your child’s situation. Read our full medical disclaimer at braincarepath.com/disclaimer/
Bibliography
- Hydrocephalus Association. Causes of Hydrocephalus. Available at: https://www.hydroassoc.org/
- National Institute of Neurological Disorders and Stroke. Dandy-Walker Malformation Information Page. Available at: https://www.ninds.nih.gov/
- National Organization for Rare Disorders. Aqueductal Stenosis. Available at: https://rarediseases.org/